When I moved back to Canada from the USA - it was a bit of an adjustment to what you can and can't get off the shelves at the drugstore.
I remember in the early 80s, telling the MD I saw in Hawaii on vacation, that I would just go to the drugstore to buy the benadryl for my swollen eye - and he looked at me like I just told him I was a drug abuser.
"You can't get that off the shelf - you need a prescription for it" he told me.
That was news to me - in Canada, at that time, you could just get it off the shelf, just as you could the ibuprofen.
Same with codeine. You can still buy acetaminophen with 8 mg of codeine over the counter without an Rx. Mersyndol is one of my favorites.....it has an antihistamine in it as well as the codeine. Expensive at $23 a bottle of 100's but a very good medication for migraines.
So,skipping back to the move home to Canada:
I was in the local pharmacy, and after waiting the 2 or 3 persons ahead of me in the lineup to speak to the pharmacist - I asked the ill-fated question:
"Where on the shelves do you put the Monistat?" - not realizing that it wasn't available except by Rx in Canada at that time.
I had spent a good half hour looking down every aisle for that life-saving medication.
Loud enough so the entire drugstore could hear, he announced:
"Dear - you need a doctor to prescribe you Monistat - it's NOT an OTC..."
I was humiliated. I started to back away, embarrassed to the point of wanting to run.
Then - He stepped forward.
"Hi" He said. " Would you like me to write you a prescription?"
I looked over at the kindly face and recognized him instantly as one of the docs that occasionally came to do deliveries and must have recognized me from the Labor Delivery unit. He had been in the lineup behind me, and - along with the rest of the crowd - overheard the conversation with the Pharmacist.
"Uh. Oh sure! Thanks so much! " I was relieved and mortified at the same time.
Later, back on the Labor Delivery unit at work, I asked him if he was taking on new patients.
"Certainly - for a colleague " he replied.
And so our relationship began.
He was thebest MD. You couldn't ask for a kinder and thoughtful MD. He was soft-spoken and meticulous in his practice. AND - his deliveries were always so quiet and relaxed.
We called him "the Midwife Doc" because the deliveries he attended were so lovely.
I can still picture him sitting on the lowered foot of the bed as he was getting ready for the delivery of a baby on our L&D unit. The lights in the room were off - except for the soft glow of a portable lamp next to his elbow.
There was a warm quiet in the room. He spoke softly and encouragingly to the woman as she pushed in her own style - lying on her side on the unbroken bed, husband next to mom, holding her leg during the little pushes. Midwife Doc patiently waited, supporting the perineum as the baby's head slowly pushed it's way through - crowning ever so slowly.
Each 5 minute interval Doppler tone had a reassuring - *dop*dop*dop* - as we encouraged the mom.
No loud noises.
No counting.
Just mom and quiet words........
He never panicked. He didn't see the need for an episiotomy. He looked up me and then over at mom and said casually, "Well, nurse, how is everyone doing?" Twinkle in his eye.
I looked at the mom - face glowing with sweat, but a serene smile on her face.
"Perfect. Just perfect" I replied.
In the next few minutes, the baby easily slid out.....
A month later - it only took one little mistake to change everything.
On the way home from attending a delivery, Midwife Doc was talking on his cell phone as he drove along one of the little town's streets.
He didn't see his red light at the intersection.
His sturdy car was T-boned, and he was thrown half a block away, through the side window and out of his car - unconscious.
As talk in the town would have it - his GCS scoring on arrival in ER was the lowest it could be. There wasn't a person in the entire hospital that didn't feel sick about the accident.
He had little kids - and in fact, I still had the thank-you note from when I had attended at the delivery of his baby that same year.
People that had never prayed before, prayed fervently for this kind doctor.
Miraculously he did recover, but unfortunately, never to the point where he could go back to his practice.
I saw him in passing in the community several times. There was a blank look in his eyes. Not even a little sparkle. No recognition of me, or anyone else. Still the same kind face - but no longer the man I knew.
You could tell he was trying to remember, but he just couldn't quite get there.
His entire life - as he and his family knew it - was destroyed.
He no longer had a means of employment.
He was alive, yes. He still recognised his children and wife....but he no longer had the same joy and was no longer able to follow conversations or remember ..... and definitely all knowledge of his medical training had disappeared.
This tragedy happened at the time when cell phones were just emerging, and no thought or concern was given to talking on a cell while driving. It was just the beginning of many such accidents to come in the community and the country.
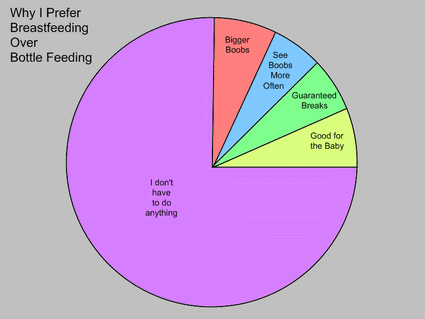
I was over at the Man-Nurse Diaries reading some of his past blogposts. I ran across this one - "Dad's Prefer Breast Feeding" and had to chuckle - especially when I looked at his pie chart on why....
It reminded me of a story my mother told me once a while back (she would kill me if she knew I was repeating this, but, uh, oh well - there isn't anyone I know reading this anyway, except for my girlfriend Jan- and she knows everything about my screwball family so it's gonna be no big news to her!)
It is one of mom's own breastfeeding stories.
My mother breast fed all of her children - all five of us - in an era that encouraged bottlefeeding - the 1950s. Or - should I say - actively discouraged breast feeding, so I am quite proud of mom for doing what she thought right when there was so much pressure around her to give it up or made to feel somehow that it was wrong. It seems that milk production was not a problem for the women in her family. She took to it really well.
So well, it seems, that at times she sometimes had too much milk - if there is such a problem. (which Idon't believe!) What to do when there was no baby around to feed and there is a little bit of excess and she isn't (for some unknown reason) wanting to pump and save?
So - fast forward to many years later when mom was in a group of women from her church who were discussing breast feeding. The Pastor's wife had just had her baby and it seems that she had the very same "problem".
Of course she asked my mother, being the experienced and wise sage in the women's group, what she did when the milk was overflowing and there was no baby to put to the breast.
Mom paused, slightly embarrassed.
"Oh, my husband took care of that" she replied sheepishly with a little smile.
My last posting of May - May 29th. I thought since there have been a few deaths recently related to medication errors, I would repost this. This is what happens when people jump to conclusions and investigations are not carried out properly. It is easy to point fingers at the suspect, but what happens when you actually are innocent and everyone assumes you are guilty? There but for the grace of god...... Here is a young nurse's story - the one that rocked our nursing world back in the early 1980s.
When I was a young nurse back in 1981-1982, a Canadian court case shocked the nursing community. It was enough to have every nurse in Canada take stock of their vulnerability.
It was discovered that there was a higher than average death rate in a certain Pediatric Cardiac Unit at Toronto's Sick Kids Hospital. Up to 46 babies died "suspiciously". An MD told his friends, then went to the police - "Someone's killing our kids" he claimed.
You can read all about it if you google "Susan Nelles nurse". She was accused of murdering 4 babies. All the evidence was circumstantial. Yet, she was arrested and hauled away by the police and incarcerated until the judge exonerated her due to insufficient evidence almost a year later. The biggest part of the prosecutors case rested on her close vicinity to the Unit plus the above MD's observation that she wasn't sufficiently grief stricken - according to his standards - while she was doing end of shift paperwork in the am on the deceased baby's chart.
Turns out that she wasn't even there for 3 out of the four suspected "homicides" ....and the MD had no clue what the RN was like, never having spent more than a few moments with her. Also, it was found that the test that detected digoxin - the suspected killer - was not only experimental, but flawed. Yet, because of the proceedings, her reputation was damaged and it caused stress to her family - enough stress that her father, an MD , died of cardiac arrest during the proceedings.
Her legal costs back then exceeded $200K which was the price of 3 average homes.
She lost almost a year of her life, spent under a microscope and denied a normal life. The newspapers reported extensively on it and people were ready to play judge and jury, calling for "justice" to be rendered on this nurse.
She was stripped of dignity, privacy and her reputation. You can still find her name in thesis', newspaper articles online and general hits.....1,710 google results for "Susan Nelles nurse"....her notoriety just won't die. In March 1991 the Halifax Chronicle Herald reported that she was still "haunted" by the accusations of murder that had been made against her.
Circumstantial Evidence.
Imagine - you could end up in Jail for a good chunk of time because coincidence sets you the wrong place at the wrong time ( although not as many times by a long shot as another nurse who was later under suspicion but no charges laid).
Then, because you have a law student as a roommate, and she suggests you should see a nurse liability lawyer because of the "talk" about the unit and gives you a couple of phone numbers, and when the police come to question you - you mention that you wish to contact a lawyer first and you pull out those handy phone numbers - the police think you are exhibiting "suspicious behavior".
Then an MD that flies through your unit once in a while feels compelled to testify about your "lack of grief" and the "scene of the crime" has been disposed of due to hospital inattention despite all the suspicions.
Oh, but you say - that was almost 30 years ago.
Think it couldn't happen today?
Take a look at Lucy De Berk, the Dutch RN that was recently - in this past decade - incarcerated for 6 1/2 years, convicted of serial murders (7) with the "proof" based on incorrect statistical data, wrongly analysed and wrongly interpreted by a statistician.
There were no eyewitnesses or evidence found. Only the statistical improbability of babies dying on her shift. In the end, all the deaths were attributed to "natural" causes. No evidence whatsoever. Just stats and somebody's say-so.
But, the damage remains. It took a physical toll on De Berk. She suffered a stroke while incarcerated. It also took a toll on her personal life. As a newspaper reports: "On Wednesday the Arnhem court is expected to conclude the case by declaring her innocent of the murders, a course of action urged on the court by the public prosecutors.
It should bring to an end one of the worst miscarriages of justice in Dutch history, but will it clear her name? Many Dutch people appear unpersuaded." The public don't see the injustice of it all. She will still have to deal with this - probably for the rest of her life.
The thought that a nurse that is innocent can be hauled up before the courts and judged by society, still gives me a chill. I am fairly careful in what I say out loud in the hospital. I might think some things......who doesn't.....but what comes out of my mouth in a hospital setting is fairly measured.
I am uber-careful with my charting, drugs and such. But how do you protect yourself when you have done nothing wrong?
Interestingly enough, through the whole process, who was the most to blame for the accusations?
Points to be pondered: 1. Although the deaths increased in the Cardiac unit, the overall deaths in the hospital did not. Why? Apparently babies were being moved out of the ICU before they should have been and put on the Cardiac Unit.
After Nelles arrest, the hospital changed the policy to keep the patients in ICU longer post operative. So, statistically speaking, post arrest - there was a dramatic decrease in the deaths on the Cardiac Unit itself, but overall - no change. The hospital had just redistributed the deaths to the ICU, but in the process- further incriminated Nelles.
2.The supposed presence of digoxin may well have never existed. In the Nelles case, the tests the courts relied on to detect digoxin in the deceased and exhumed babies were experimental and was proved to show false positives. It was actually impossible to test whether digoxin was even present.
Also, hospital policy dictated that bodies be cleaned off, IV tubing dumped and bedding around the baby sent to laundry etc....therefore perhaps critical evidence discarded - evidence that may have cleared Nelles immediately.
3. The Dutch Nurse? Statistics and psychology drove this case. De Berk's conviction - and even the 'proof' that there were any murders at all – let alone by whom – were almost entirely based on flawed data and flawed interpretation.
Apparently the traces of toxins found in the bodies of the deceased in this case could have been residual from treatments done. There was no evidence linking De Berk to any of the deaths except she was on shift at the time of expiration - and the stats showed that there were more deaths on her shift by chance than could be statistically proved possible.
4. Convinced she was guilty, the police and the managers of the Juliana Children's Hospital assembled a compendium of "data" in which it seemed every death became unnatural when it had occurred during, or after, a shift in which she had worked. For one of the alleged murders, it was established on appeal she had not even been in the hospital for three days around the time it occurred.
Their saving grace?:
1. The nurses working with Nelles all supported Nelles throughout, testifying opposite of what the MD did....which was a major factor in the judge dismissing all charges. Their solidarity in blaming hospital policy went far to exonerate Nelles. No thanks to the one MD (Dr Fowler) who seemed insistent on pushing his theory of guilt by facial expression.
2. The determination of a statistical mathematician at a Leiden University that believed De Berk was innocent, was the driving force behind clinching an overturn in De Berk's case. Finally an expert was brought in to debunk the theories in the prosecutors argument - the flawed testing.
Conclusion:
Sometimes, in the process of finding answers for the public, Management may use you as a scapegoat. You hope that your hospital will back you when the time comes, but don't count on it.
As both these nurses above found out - Nurses, in the eyes of the management, when under fire - are expendable.
This isn't the only conclusion you can draw from this .... but the obvious message seems pretty clear to me.
******************************************
A little post script here: Apparently, according to the published report in the Ottawa Citizen, the prosecutors stated that if the judge had found sufficient evidence to proceed to trial in the Susan Nelles case, they would have dropped the case because the outcome would not have been in their favor - and they didn't want to put Ms Nelles through the pain and suffering of a drawn out trial.
Does anyone really understand that kind of reasoning???......
Definitely a travesty of justice.
And I agree about MD Fowler. If you clicked on the link and read the actual transcript of the questioning....he is majorly a douche. I tried to google his name but nothing comes up. Perhaps he is not "of this earth" at this time. It sure is quite the mark to leave on this earth...the only reference to him is that record of his statement.....his douchebagness on display for posterity.
Funny that when I moved to California (East Bay to be exact) - I would experience 3 seperate disasters. Everything comes in THREES. But I had no idea that meant absolutely EVERYTHING.
I have just reposted my old entries from June 2, June 15 and June 16 which I retell the stories of the 3 Natural Disasters I lived through while living in "The Golden State". Not so golden for me. But ONE thing it did for me was give me the training for Labor and Delivery..... and for that I am very thankful.
If you would like to re-read these revamped, relaundered and renewed posts.....or if you have never read them before - WELCOME - just follow these three links:
By the way. I am STILL accepting names for the FREE BOOK. Let me know if you would like this book to give to someone!!! (yes I can have it sent to you so you can gift it to whomever you wish!) Last chance is September 30. Just click on the book in the RIGHT COLUMN.
Holy cow. Or as my uncle (may he rest in peace) - always said "Holy Mackerel!"
I can't believe that! When did I get this old? Where did the time go? WTFlip????
It was just yesterday that the first blush of nursing took hold of me.....and I was afraid of killing patients. Now I just want to get through the day without killing myself. Funny how the old body just decides to turn on me. I used to run relays and was the Interior Provincial Javelin throwing champion. I hiked up mountains, biked where I wanted to go and walked miles and miles.....
It could be worse. At least I have all my faculties about me. The neurons are synapsing in an orderly fashion - for me, anyway.
I was just having this convo with my Nurse Cousin from Texas.....
When I was a young thing, I used to wonder how the old people I looked after couldn't see all those hairs growing off their nose or out their nostrils or ears, the extra huge eyebrows that were never plucked and wondered how they didn't know there were growths coming out of their face......you know, all that grooming that needs to be kept up with.....
And now, with the help of my 25X mirror.....I *know* why......
They couldn't see anything up close. Glasses can only do so much. When it comes right down to it....ya really need a 25X mirror to see everything .....
And..... Holy Mackerel. FIVE DECADES...............
One of my readers made a comment about Float Nursing - how the thought makes her cringe. My reply? If you start doing it at the beginning of your career....it is a lot easier.
You see, as you get more comfortable with nursing....and it becomes routine...and you stay in the same hospital, the same ward, the same shifts.....the less comfortable you feel when taken out of that comfort zone. That's only normal. I have always been the restless type (I guess that is why I have moved 10 or more times in 10 years! Since married four years ago...this is the longest I have stayed in one place!) so I suppose that is why I have always felt the need to move around. I am actually almost envious of those nurses that have been able to stay in one place. But that is just who I am. A restless soul.
Or - at least I was.
Now, I am quite content to do the same job, the same house, the same thing......OK - well - not always. Sometimes I must admit that familiar feeling of restlessness creeps up on me and I tell my husband - "Let's move....I don't want to live here anymore".....but he has learned to ignore me and just let me rant and rave.....because I will always settle down again. Back to the routine.
Old habits die hard.
AND - I am much too close to retirement at this point to start jeopardizing my pension. Meanwhile, here is my old post from May 12 :
Tattoos and Float Nursing
I gotta rush through this. It's a nice day outside - my outside thermometer says 90F - and I want to take advantage while it lasts.
When I started working casual (part time hospital, part time department store nurse) I was floated around the hospital wherever I was needed.
Floating around is fun and interesting. You get to go different places and it keeps you on your toes, you learn a lot of new things and it definitely isn't boring or routine. Problem is, though, the end of the day leaves you wondering what the heck you did. There is no assignment per say and although you know that you just took care of pretty well every dirty assignment that no one else wanted to do on almost every unit, you just feel like you accomplished nothing. The only thing that reassures you that you actually worked was your complete exhaustion at the end of your shift.
The up side was, you usually got off on time because there was no report to give and no patient assignment that you had to keep an eye out on while the oncoming staff was taking report. I really quite enjoyed the freedom to float around. There was always something to do everywhere you went and the nurses were usually really glad to see you.....and having worked in that same hospital for 12 years, there was pretty well no place I hadn't been and no one that I hadn't gotten to know. It was a social type job, in other words. For me, anyway.
When I was a student, because I knew the RNs that were preceptoring me from my working-as-an-LPN stint, I got tons of opportunities to start IVs - even difficult ones, and I became quite proficient as a result.....so one of the things I would do as a new nurse and a float was to run around starting IVs that other RNs couldn't get. This skill would later come in handy for when I dabbled in Prison Nursing (ya that too - I will tell you about that later)
Occasionally you got to replace a staff member that called in sick and work the entire day on one unit. Telemetry was one of them. I took a course on reading strips and was starting to get pretty good at the monitors before I escaped town for California. Like I said before, I loved to learn new things. It was interesting to say the least. However, the patient that I most remembered wasn't the usual step-down-unit-type. Here is the story:
Three kids decided they were going to get tattoos. I am not adverse to tattoos. Quite the opposite. I can appreciate a well placed tattoo and having worked OB - I've had the privilege of seeing LOTS of those-not-seen-by-others.
On the other hand, my girlfriend Jan is appalled with the appearance of that type of artwork, but I am suspecting it has a lot to do with the "connotations" in her mind (prison). Much to my girlfriend's chagrin, her son is covered with Lovely Tattoos (yes, and even the name of his mother on his back-she should at least appreciate that! I think it's sweet...) and for a while, he owned a tattoo parlour that I would later tease her to come visit with me for matching BFF tattoos.
Esthetically, tattoos can be quite pretty. Or interesting. Or "fun". I once had a patient on the Surgical Unit that had a tattoo of a naked woman on his arm. Interestingly enough, the only vein available that I could get at easily was right between the legs. He thought that was amusing. I was just doing my job.
Personally, the functional tattoo is my preference. I admit at this point that I have tattoos - albeit not the traditional type - eyeliner and lip color. Sounds funny for someone that has a needle phobia to wish a tattoo on themselves - but I was desperate.
I am a hazel eyed blonde. I naturally lack skin color where it should be. Without makeup, I look sick. I have absolutely NO natural color in my lips. None. Zip. It was a chore getting up early to put on makeup pre-shift just to keep concerned colleagues from constantly asking me - are you OK??You LOOK SICK!!! - so when I found out you could have makeup applied permanently - I jumped on it.
In my excitement to have permanent lips and liner - I was in denial as to how one gets a tattoo. For some reason, right up until I sat in the esthetician's chair, I shut out that little piece of info - to have a tattoo done, they have to use a needle. Eighteen years ago I got my lips tattooed - and not just once, but Twice - because the first time didn't fully take and I had no base color to start with.
YOUTUBE TATTOO PLAYLAND AD:
I happened to have a little tube of Emla, a handy little topical anesthesia, to numb my lips. Unfortunately, my memory isn't so good for non-nursing things or self medication, and it overrode my needle phobia. Five minutes outside of Sausilito, I realized I had forgotten to apply the Emla. Coming out of the esthetician's office, I ran into another gal who *loaned* me a vicodin which I promptly washed down with a glass of white wine supplied by the esthetician. I might have well popped an M&M and washed it down with a glass of water. At this point I was questioning the irrational decision to decline the offer for an anesthesiologist's services. A second glass of wine later, I braved the worst.
I have to say, I have never felt anything so painful. Of course, I have never experienced childbirth so my experience of the pain spectrum probably isn't at it's most upper limit. But, at the time, it seemed that every single nerve ending was located in my lips. The gal used 10% lidocaine as she went along but nothing really touched that "discomfort" -a nurse's synonym for outright excruciating pain.
The stupid thing about this is...knowing how much pain is inflicted, you would think I would do anything to avoid a repeat. I guess I developed selective amnesia over the years, and 12 months ago, decided it would be great to have permanent eyeliner applied. Stupid, stupid, stupid. Ok, so now I understand some of my clients who do dumb things more than once.....
I tell you this story because, getting back to the three kids getting tattoos.....they did them themselves. Unfortunately, they decided to share the tattoo needle. Not very bright. In my time working in a prison, you see what happens when tattoo needles are shared - half the population end up with Hep C and if you are really unlucky - you get Hep B - which IMO is almost as bad as HIV.
I guess the kids thought they were safe since they were only sharing the tattoo needle between themselves. What these kids didn't realize was - it was more than the needle they shared. One kid was a diabetic. The other was healthy. The third had Hepatitis B. Not smart. We only got two of the kids because the third one, the "healthy" one - died within a week. The diabetic gal was very very sick and spent a long time recovering. I got her right near the end of her hospital stay.
I am not sure what happened with the one that was the carrier, but I believe he was one of her many "visitors". It was interesting to see their non-reaction to the death of their friend, the constant partying and tomfoolery that went on in that room. Maybe it was denial, and I can understand that. But - It didn't seem to click that what they did was downright dangerous and why. I think it has to do with how invincible you feel when you are young. That feeling dissipates with age. The "it will never happen to me" starts to turn into "when is it going to happen to me".
Moral of the story today is, if you have kids that want to get a tattoo.....it is better to buy them a "proper" one...maybe negotiate a smaller one that they can hide or remove easily when they get older and wiser... and inspect the facilities and ensure that they are getting one that is going to not only have appropriate placement, but that the equipment used is properly sterilized.
As much as you hate it.....it will protect them from themselves. There are always people ( like me) that - no matter how much evidence is present - they're gonna do it anyway. Which - reminds me.
I have to phone my esthetician and get my permanent eyeliner touched up. I have been putting it off for a year now.
Time to pay the piper.
Posted by A NURSE at 6:52 AM
Once again, lucky for me, this time the comments were saved:
2 comments:
newnurseinthehood said...
Amen. My husband has a sleeve and half of beautiful work, and people always seem to want to talk to him about it, but the majority seem to freak when he answers about what he paid for it and then throw out the name of some nasty shop or mention that they know a guy who does it in his living room. Seriously? It's worth it to pay for good, custom work. Not only do you not want hep C, but that is going to be on you forever. Why not pay the money for an artist who is actually good?
Also- eyes- zoinks. I thought getting my ribs and side done was bad.
May 12, 2010 12:22 PM
A NURSE said...
I paid $400 for my lips. And that was almost 20 years ago. I think it was $300 for my eyeliner. What we do for "beauty" and convenience. But definitely - It pays to do it the "right" way....:)
May 12, 2010 1:23 PM
Yes. Those were the days. We don't really know or realize what the new settlers went through - just to live - a mere 100 years ago. We take a lot for granted....and sometimes I wonder what it would have been like living in that dusty prairie town in Alberta....as a new immigrant - just like my Grandparents.
It must have been painful for G&G to leave family behind, especially since - when they said their goodbyes - it may very will be the last time they saw any family again, as it was no easy feat to travel to Europe and back without a lot of planning and a month or two of time. Trying to comfort her, my Grandmother's mama told her " Just look at the stars at night. I will be looking at the same sky...."
There is nothing more breathtaking than the expansive vault of heaven filled with twinkling lights. My Grandmother wrote of it in her memoirs. Often she would beckon her new husband out to the porch to watch the night sky. No tv. No radio. No telephone or cell phone. Just the painful quietness and the sparkling celestial diamonds adorning the black curtain of nature surrounding them.
And - every summer they could see the spectacular colourful show of nature - the Northern Lights - as they danced across the expansive night sky - rolling along - fading - just to flash in multi-colours above their head. It was awe-inspiring. Better than any movie!
Whenever I hear this song....I think of my grandparents out on the prairie, living in that tiny 16ft by 26 ft shack my Grandfather built himself....
Halley's Comet: When it came around in 1986 - I remember clearly seeing it's tail fly across the sky. Nineteen eighty-six was also the year my Grandmother died - at age 91.
The one thing she wanted was to die at home with her husband by her side - and a view of that starry sky. I was willing to stay with them in their apartment until the end. As a fellow Nurse and, most importantly, her Granddaughter, I thought it the least I could do.
The MD said there was no way he could "accommodate" this. Dying at home was only just coming into "vogue" - and was still discouraged in most medical circles. The cold four walls of the hospital was all she saw as she left this earth.
It was at that moment that I realized that, with all the progress of medicine, compassion was somehow lost along the way.
On another note, if I live to see the next time Halley's comes around....I will be 110.
I am not holding my breath.
****
Halley Came To Jackson (lyrics) Songwriter: Mary Chapin-Carpenter
Late one night when the wind was still Daddy brought the baby to the window sill To see a bit of heaven shoot across the sky The one and only time Daddy saw it fly
It came from the east just as bright as a torch The neighbors had a party on their porch Daddy rocked the baby, Mother said "amen" When Halley came to visit in nineteen ten
Now back then Jackson was a real small town And it's not every night a comet comes around It was almost eighty years since its last time through So I bet your mother would've said "amen" too
As its tail stretched out like a stardust streak The papers wrote about it every day for a week They wondered where it's going and where it's been When Halley came to Jackson in 1910
Now Daddy told the baby sleeping in his arms To dream a little dream of a comet's charms And he made a little wish as she slept so sound In nineteen eighty-six that wish came 'round
It came from the east, just as bright as a torch She saw it in the sky from her daddy's porch As heavenly sent as it was back then When Halley came to Jackson in nineteen ten Late one night when the wind was still
OH! and one other tidbit. Found this recent ad for a "Department Store Nurse" in Davao City in the Philippines. I am wondering - how much do they pay an RN over there? Here is the ad:
Company Nurse at Victoria Department Store in Davao City (posted on 08-19-2010)
Filed under Healthcare & Nursing
•Female, Single, not more than 28 years old
•Graduate of BS nursing, NLE passer
•Related experience is an advantage
*Can work under pressure (obviously, this is not a job offering in Canada where you can't discriminate by age, sex or marital status. And...wtflip is the "can work under pressure"thing??? From my experience, Store Nursing is on the stress level of a Walmart greeter......yes, I actually admit that. That is why it was so much fun...because it wasn't stressful in the least - and I got paid for it! Closest I have ever come to getting paid for doing nothing - so to speak. At least - that's what it felt like. I wonder what goes on in Filipino Malls that it would be so stressful???)
AND: here is a partial article from the American Journal of Nursing 1941 - a peek into the life of a Department Store Nurse in New York - "From Teakettle to Busy Medical Department". Really. I suppose Cherry Ames book Department Store Nurse's description is pretty well on the money after all. Both were written in the same year. =^@ And here I thought it was all bogus.
This is an entry from April 30th. I had injured my wrist and was resting it ....so I was typing with one finger.
I was off work a whole week, because my job is mostly computer work - which means copious typing. Not only do I do a lot of typing, but I have to do it fast, and one-handed-finger-pecking isn't considered high speed.
So, thus I painstakingly continued with the story of my life as an RN.......................
For those who really struggle as a student nurse - I have complete sympathy for you. It was no picnic, that is for sure. I had misgivings, and at times when it was rough I doubted whether I had what it takes to get there....but despite everything - I perservered, and was glad I did. Here is my account of some of what I experienced on my Road to Become an RN:
I was going through some old drawers and boxes today....and found this stack of date books.
They basically represents my career as an RN. I think I am only missing one year...and that is because it was on an *actual* BIG calendar, as opposed to a diary-book calendar. Count them. 19. Most are 2 year calendars and some are one year calendars.
I can thumb through them and see where I was on whatever day for the last 30 years. Amazing isn't it?
That all those years boil down to 19 books. Oh. And that doesn't include this years book. That is 5 decades! =^@
What it doesn't show is all those years of caring for people...hours spent worrying about their well being - miles of running up and down hallways, countless medications given out, numerous IV's hung, over 6,000 babies delivered, a billion MD orders - well - everything an RN does in a day. Or a night.
Some years were better than others. Some were washes. But I can say, I did learn a lot and did a lot in all those years. Geriatrics, Rehab, Medical, Surgical, Store Nurse, L&D, Gyne, Nursery, Psychiatry, Telemetry, Camp RN, Travel Nursing, Prison Nursing, Triage RN,Float RN, Board of director for Non-profit Seniors Assisted Living... all that packed into 19 little date books. Or 30 some odd years- whichever way you want to look at it.
I don't know why I keep them. Maybe because they are like a diary of what the biggest part of my life was....or is. I probably spent more Christmases and more holidays and more birthdays and more special times with colleagues and patients than with my own family. There are little notes here and there of things I did....travelling backpacking in Europe. Twice. A dozen or so odd trips to Hawaii. More than that to Mexico. More moves than I can count - approximately Seventeen? - within 2 different countries, with 7 homes purchased and 7 Canadian and 5 American hospitals worked in.
I Lost count long ago - of the boyfriends I dated and the friends I left behind and the roommates that moved on. But even though they are a record of the past....it's the present that means more to me.
So - was it all worth it? I think so. Although I had my misgivings many times over the years, what I chose as a career (although I didn't really ever consider it a career since it was supposed to only be temporary) made me who I am today - and I quite like where I am at the moment.
But given the opportunity to leave it for good - would I? You bet. But, for now, it is difficult to let go of what has been a major part of one's life.
And so I hang on to that dusty little pile of elastic-bound date books. And every once in a while.....I flip through them and smile........
Throught the years, my parents have done volunteer work for several non-profit organizations - working for the improvement in living conditions in various countries around the globe. They would leave for months on end. My dad worked in the construction end of things while my mom would do garden work, painting, cooking - or knitting sweaters and slippers - even caring for sick children (in a capacity of an experienced mother who had had 5 children, in the absence of medical personnel) while in those other countries.
( The plane [photo above] that flew mom into the little village [photo below] in the middle of the jungle in South America - Suriname. Quite brave of her, and definitely not something I would do!! )
I will relate to you the following vignette, which is almost unbelievable, realizing there are 6.8 billion people in the world. Although, knowing all the places around the globe my folks have visited, and all the people they have met on these trips, I am not too surprised.
Still, what are the odds?
Neighbors of my folks were on vacation in Ireland. They just happened to stop in at a small town pub in the Middle of Nowhere. It was one of those little-hole-in-the-wall places that has the menu on a chalkboard over the bar. While they were discussing what to eat, a young newlywed couple on their honeymoon from New Zealand sat at a nearby table, and they - listening to their conversation, giggling at their 'accent' - asked where they were from.
"Canada" they generalized, not for a minute thinking that anyone from the other side of the world would know where their Province was, never mind our small town, population 800. The rest of the Conversation went something like this:
"Where in Canada? We have friends from Canada" the couple queried.
"Well, British Columbia...." the folks' friends offered, hoping that sounded familiar.
" British Columbia!? Our friends are from there too! What town?"
"Oh....a small village in the interior.....in “The Great Vineyard Valley" area.
"That's where our friends are from! What town??"
"TeensyTown......" how weird was this...
TeensyTown? But - that is where our friends live! Do you know the XXXXXs (my parents)???
Needless to say, my folk's neighbors were *gobsmacked*. Unbelievable to be standing in a small town half way round the world where they only just happened to stop by chance and running into someone else from half way round the world - and both knowing my parents very well - their paths intersecting....... serendipitously.
It is definitely a small world within the nursing community here in Canada also, and although perhaps not as dramatic as the story above, still amazing. At least, in the West it is. Whenever a new nurse starts out from another Western province or town, more often than not, they will discover that one of their new colleagues knows - or has a mutual acquaintance from - either their nursing school, or a former hospital, or friends in another town. There is no getting away from it.
When I moved back from California to a whole different Canadian city and hospital than which I started out my career, I found myself working with a former classmate from nursing school and a former co-worker from the first hospital I worked in - plus several other nurses who knew people I worked with in the past.
In every hospital I worked in thereafter, there was always someone who knew - or worked with people I knew. You can't get away with much in this neck of the woods. I guarantee it. It always catches up to you. At my present job, one of my colleagues is a nurse I worked with in Seattle. Small world.
This does create a blogging problem.
I am limited to how much I can say on my blog about my present nursing job. When you are dealing with reduced numbers in population (34million est Canadian pop. vs 309 million est USA pop.) – there are always too many identifying markers when telling a story, no matter how much you try to anonymize. There just isn't enough people here to fade into the woodwork.
So, that’s why you won't find much on here about my current nursing job - except for slight mentions. I quite like my job.....it's almost like *not working* - the days I am working at home - so I don’t want to jeopardize it in any way at all - because most employers do care about what you as their employee talks about if you identify them as your employer....since they usually feel it is a reflection on their business. Unfortunately, with the Government as my employer - there isn't going to be much opportunity to choose another.
I have to say, the one thing that new nurses have nightmares about when they start their first job is killing their patients. I know I did. They haunted me as a student nurse and it only got worse the first day as an RN, stepping out onto the Surgical Unit. Back then, there were no "preceptor programs" - you were just thrown out onto the floor, on your own. Well, not totally on your own. The other RNs kept a loose eye out for you, if they weren't giving you their extra work.
Nowadays there are plenty of safety precautions in place to stop the errors before they happen. Meds are prewrapped and prelabeled, only to be dispensed if on the patient's Dr Order sheet. MARs are checked nightly (hopefully) and updated. Some hospitals use Pyxis machines that deliver specific medications that you code in and sign out with a thumbprint. Pharmaceutical companies have changed the color codes, the type of packaging and a lot of other things (usually after the barn door closes) to easily ID a medication. Most medications come up from the Pharmacy premixed and well labelled. We now administer a lot of the IV meds by IV pump so as to ensure the correct rate of administration (you don't want to know what we used to let run in free flow). In nursing school we are imprinted with this basic principle: The Right patient, the right drug and dose, the right time and route. It is quite monotonous but there is a good reason for it.
If a nurse that has been working a while says she/he hasn't made a med error ever....she/he is not telling you the truth. Most will not admit to it. Or they have repressed the incident. But, we each have our own little story that is indelibly burned in our minds that, hopefully, makes us better nurses. Statistics show that medication errors are one of the leading injurious things a patient suffers while in the hospital. "Near misses" were never usually taken note of in years past, so it makes sense that there were many mistakes or near mistakes (what we now call ADEs or Adverse Drug Events) that occurred that were never recorded. Possibly still are.
As an LPN, I remember "talk" of one RN on the Medical Unit I worked on that whisked a whole bag of saline within 10 minutes into a tiny fragile elderly woman that already had compromised multiple systems - and didn't report it. Didn't do anything about it. She just hung another bag and re-marked it and carried on. Didn't tell the MD, didn't do anything. Whispers that the expiration due to lung congestion was mostly due to that extra bag of saline. Since it has been 32 years since that incident, I have no clue who the nurse was or who the patient was. All I know is that nothing was done to correct the situation and the nurse did not admit to wrongdoing. Basically, it was swept under the carpet.
This is another story I heard after the fact, but more recently, within the last decade. On an OB unit I worked with an Airhead RN that happened to mix up a PCA syringe with an EPIDURAL syringe. BIG difference. They would have been well labelled. It was caught after the first hour when Airhead went on lunch and the covering RN checked things out immediately when the patient started complaining of weird sensations in her head and found the error. Airhead tried to blame it on whoever put the PCA syringes in the locked cupboard next to the Epidural syringes (admittedly, the hospital wasn't beyond reproach for using the same pump for both Epidurals and PCAs and the same locked cupboard for both) but the bottom line was - the patient was the one harmed, and the RN denied her part in the error.
My own story was a "near miss" and as a new grad RN, ensured for the rest of my career that I would NEVER EVER make another med error. Never. Ever. And I haven't. It still makes my skin crawl 28 years later - thinking about what could have happened. I am hoping that my own admission will caution those that think they are bulletproof. You must never take short-cuts and never think that "it could never happen to me". As recent grads, usually the concept of Standards of Nursing Care is so brand new you can't imagine making similar errors as above. But, let me tell you, one day you will come very close if not actually erring, and it could very well end up in disaster, never mind a free trip (all expenses not paid) through the court system, which you will want to avoid at all costs.
My story: This was during the time that we had 15 or so post operative patients to care for all at once, and when the other RN was on her break, that load would be double. Taking into consideration that most patients were not as acute due to the pre-early discharge era, it was still an ample assignment for one RN- and a new one at that. I was swamped, running around answering bells, getting meds, checking post op vitals, emptying/checking hemovacs, pottying hip replacements,checking toes in casts, tractions - well, anyone that has been on a general surgical unit gets my drift. I am sure I was a blur to most patients as I whizzed through their room.
There was a young woman that had been waiting to have her IV downgraded to a lock. I ran to the cupboard that held the heparin for flush. (Ya, those were the days we used diluted heparin, not saline for the flushes, thus the term "hep-lock" that you hear among "old" nurses) I grabbed the vial that looked exactly like and was marked exactly like the heparin vial from the place on the shelf labelled Heparin flush.
In those days we kept flats of different but commonly used IV vials the cupboard with a label on the shelf of what was in the box above it - you just took what you needed and diluted, mixed and drew it up yourself in a syringe or minibag - you name it - we mixed it - everything from antibiotics, Heparin drips, insulin drips, Potassium ........
Yup, you guessed it. I grabbed a vial of Potassium. I drew up the required amount in a hurry to get to the next task - ran to the room with that Potassium filled syringe, ready to flush the lock. To this day, I don't know what made me stop as I put the needle into the port ( no such thing in those days as "needleless systems") but I thank the "New Nurse Angel" on my shoulder for that "second thinking". I don't know whether it was because the chatty little patient had asked something about the lock, or whether it just miraculously flew through my head that I didn't double check the vial as closely as I usually did.....but I stopped before the plunge, withdrew the syringe and told the patient, one minute while I go and check something. Those were my exact words....
I ran back to the nursing station heart in my throat and looked at the place in the cupboard where the heparin vials are usually kept - above the label HEPARIN on the edge of the shelf. Someone had swapped the places of the heparin and the potassium. In those days the Flush Heparin and the Potassium Vials looked exactly alike – same size/shape/color – even the printing. Sick to my stomach and my heart beating out of my chest, with a shaking hand I shot the K from the syringe into the sink, grabbed a new syringe and heparin vial and drew up the correct flush.
I came one thumb-push from possibly killing someone. It scared me so badly, I can still picture the room, the young woman sitting cross-legged on her bed, the works - just thinking about it - I can even remember the odd color of yellow with brown splashes of who-knows-what on the med room walls and the taste of the med as it hit the sink and aerosolled into the air with the waste.......
In no particular order:
Number one : Check, check and double check. Statistically, the administration of the meds are the second most common reason for AEDs. (wait until you see the number ONE reason. It might shock you) You have heard to check the name on the MAR and the patient hospital band. But -ALSO - If a patient states "I have never taken this pill/shot before": check it out. If a patient questions "what is this pill" and you don't know: check it out (you should have already done this anyway!). If a patient says: "I already got/took this shot/pill" check it out. Ask around. You never know- sometimes meds are given by someone else answering a light when you are busy for a half an hour in another room - and not charted it right away - or at all. They should be. But you just can't count on it.
Number two: If you make a mistake, own up to it and let the charge/MD know right away. There are forms to fill out, counselling with your manager and depending on the facility - reams of other various "stuff" that ensues, but the other option is - it could kill your patient - or not. And quite possibly, there is an antidote, or at the very least, an MD that says "don't worry, that dose won't kill them, it's OK, I will just change the order".
Think of the little twins of the celebrity that could have suffered irreparable damage due to a med error from a care giver if it hadn't been found in time and admitted to.
Number three: The only one you can trust to ensure giving the correct medication is yourself. In other words, don't give a patient a drug that someone hands you because they said you should. You will see other RNs do it. It might even make you a little unpopular or might make others think you are paranoid, but refusing to give a med that is unlabelled or predrawn by someone else - may save your career one day. No matter how much you can trust another nurse and her skills - if she tries to hand you a med for you to dole out to her patient on your way down the hall - or no matter how busy you are that you really can't take the time to get or mix your own.....only trust what you have checked and drawn. Ok, there are times when syringes are well-labelled not coming from the Pharm ..... still - if I am giving a medication, I would rather that nurse waste her own mix - or she can keep it for later use if she is getting that patient back - and I will mix my own. Most nurses aren't - or shouldn't be -offended.
Number four: Know your drugs. And if you don't - Pharmacists are your friends. You can't know ALL the drugs and what they do and all the side effects. And there are so many new drugs and new studies that come out.. but... If you don't know what it is and what it is for - don't give it first and look later. I know I sort of said that in #1 but it bears an extra mention. Look it up NOW - BEFORE you give it - not after. Ya, we all would rather have someone else tell us what it is and what it does, but there is nothing like looking it up yourself that helps you remember for the next time. It can be cumbersome, but there are easy ways to do this nowadays.
Number five: Don't assume what the MD wrote is the correct dosage. Statistically, this is the main cause of ADEs. Even the Pharmacy is occasionally known to send up the wrong drug or mislabeled medication. You are responsible for what you give, including something transposed, written or calculated incorrectly. If it looks strange - ask about it or look it up. If it is a different dosage, there must be a good reason why the drug is given in this dosage or this particular way, and you might want to know this important piece of information while looking after your patient. There are all kinds of "off label" uses for different medications as well as different doses. (for instance, not only is propanolol used as an antihypertensive, it is often used for the treatment of PTSD to calm that "flight and fight" thing your body does. Recently in another nurse's blog who was wondering why the MD gave the patient benadryl for an extrapyramidal reaction to thorazine drug - because it does the same thing as cogentin - counters the effects )
Number five: Don't depend on any of the safety precautions in place to prevent medication errors. We as the direct caregivers are the best and last barrier to prevent "untoward happenings" in the system.
Some RNs will say bullshit....but they aren't gonna be the ones in court taking the hit for you....it's YOUR license on the line.
Now....let me at my Bailey's and coffee............second thought.....forget the coffee.
So I get an email from my best friend who is also an RN (we were neighbors at age 10 -45 years ago! ) and she is all pissy because.... why didn't I blog about "our" experience in the local ER......meaning - why didn't I spill my guts about my visit with my gallstones while she flitted around being the social butterfly in ER while I was writhing around in pain?
Ok- so I exaggerate - but it makes for an interesting story....and my friend loves a good story. We have a habit of rating our stories - 0 to 10 - how good was it???...so we have gotten to be fairly good storytellers.
So here goes. And. Just to warn you in advance.... I have to drive to the interior tomorrow to care for my mom post operative hip replacement.....do the " nurse" thing to ensure she makes it through her hospital surgery.... so I won't be online for a couple days.
I am sure I will have stories when I return.
So last year about this time I was having severe upper GI type pain. Being an RN what is the first thing one does? Yup. Denial. Ok. This is indigestion. It will go away.....This must have gone on - oh, say...for a month or so before it got so bad I was scaring myself into thinking I might even be having a heart attack. I ended up working my shifts scheduled, taking frequent breaks, which is - believe it or not - encouraged in my line of nursing work. It actually is a really nice job. I almost hate not to work.
Anyway....I called up my Nurse Girlfriend (I will call her Jan for short), who was an ER RN since the age of dinosaurs just like me......and together, over the phone, we tried to figure out the source of the pain. I had already tried Tagamet, Mersyndol, Gravol(Dramamine for you Americans out there!), Peptobismol, Mylanta....you name it. Anything I had in my medicine cabinet, I tried. Jan suggested a "pink lady". So, I did some bartending moves with my stashed lidocaine from a previous tattoo (will tell you about that later) and made myself a pink lady. Nope. Still had pain.
What to do next?
Jan suggested Pariet. She "just happened" to have some leftover......could I drive over and get it? (I know what you are thinking at this point....here are 2 RNs breaking every rule...) I was thinking, the last thing I really wanna do is get in my car and drive anywhere. But - since she was nice enough to offer...I thought I had might as well take her up on it - and what the heck - help myself to anything else in her medicine cabinet – I felt like I was gonna die anyway. Anything to get rid of the pain at this point. And anything to stay away from ER. I reasoned, if the pain got so much worse, her house was on the way to the hospital and I could easily make a quick detour. No problem.
Don't worry honey, I told my husband, I will be back in a few minutes.....no,no,no...really. You don't need to drive me....I'm ok..... what was I thinking??
I think that night was the worst in my life. Not only did I try the pariet, but also the Ondansetron Jan gave me ($50 per pill) - and by morning I was a wreck. No relief. There was nothing left to do but visit the Dreaded Hospital. Jan had worked in that very hospital for - what - thirty some odd million years....and none of the stories I heard her tell were very good. I figured at this point I was as good as dead.
Jan offered to come with me to ER to sit with me and make the visit a little "easier" on me, because she stated that she knew "everybody " there - like that was supposed to help. So...I drove over to Jan's and her husband dropped the two of us off in ER and I checked in. I guess I didn't show my actual pain level very well because for the next 4 hours I sat and watched people who walked in the door after me admitted to an ER cubicle with waay less urgent symptoms than myself (how did I know this? Jan did a little Q&A triage around the room, much to my chagrin).
Funny how, as a nurse, you tend to assess people and triage them......which at this point wasn't helpful to my situation at all. Jan actually knew most of the people in ER waiting to be seen ( ya don't live in the same town for 30 plus years and NOT know half the town) so she was busy visiting - with a clandestine motive of course - finding out what the others were there for, and what were their symptoms - all the questions - then proceeds to tell me how she thought I should be going in waaaaaaaaay before all the others.....maybe she just did that to make me feel better. Anyhoo.
By the 5th hour I hadn't improved. I told Jan....ya know....I actually have chest pain....and we both gave each other that deer-in-the-headlights look, knowing full well what that meant in an ER. I neglected to mention this little fact on admission.....what with the pain I was having abdominally .... and now how stupid would I look telling them at this juncture. I complain about my patients that I triage doing the same thing. I could already see them rolling their eyeballs ........whispering and pointing....."ya know that nurse sitting over there on that stretcher.....????"
When I finally got a stretcher (last patient in the waiting room) I whispered quietly to the RN...I hate to tell you this, but I have chest pain as well.... to which Jan volunteers to the whole room, "Ya and she's had it all along but didn't want to say anything because we thought you would think we were trying to line jump".
Great. Just what friends are for.
So in comes the 12 lead lines, the MD, the lab tech, the IV and the whole flurry of activity that ensues when someone whispers *chest pain*. Honestly, I really don't think it is cardiac, doc....we told them of everything we had tried so far - every last concoction.
At least we eliminated other things they would have tried and sent me home with.
When cardiac was ruled out (see, I knew it wasn't) I was shipped off to u/s and a scan was done of my gallbladder and other corresponding parts. While my friend flitted about socializing, I got the news from the ER doc. "You are the healthiest looking pancreatitis I have ever seen......" I guess all he usually sees is an assortment of alcoholics and druggies and such......not your average walky-talky-generally-healthy local nurse.....
I was discharged with a requisition for a CT scan in the next couple days plus all my ER workup and ER doc/nurse notes and an RX for buscopan – which didn’t work. I remember thinking, it couldn't be pancreatitis. It's probably my gallbladder...... of course I was right. My surgeon confirmed it.
I was due to take a trip to Hawaii the following week and the last thing I wanted to have happen was end up in an ER in Hawaii with the same thing. Should I cancel? Should I go? What would be the worst thing to happen? I was fully covered, not only with my insurance from work and my husband’s insurance - but also extra travel insurance....I could even have pre-existing illness and still have full coverage. Deluxe coverage, in fact, according to the nice lady on the phone at Blue Cross who gave her advice - Better to be in pain under a palm tree on a beach rather than at home. So I went. I am happy to say, I only had 2 bouts of pain and they were nowhere near what I had experienced at home, and it didn't even require a hospital or MD visit.
Having got that trip under my belt, my husband and I decided we also take a chance on my health and go for a trip to Washington State to visit his family for Easter. This trip didn't go as well. Second day there I developed severe abdominal pain again.....AND chest pain.... so half way through my husband's golf game I called him and told him to come and get me and take me to ER.
I have to say, my experience in an American ER was quite satisfying. This time I admitted to the gals at the desk that I had chest pain too - "but don't worry - it isn't cardiac...." I tried to reassure them. Actually, an aide at the entrance noticed me clutching my chest as I came into ER, so already had a wheelchair ready for me. She anxiously paused with me at the Receptionist desk, where I took several minutes to hand over my 4 different medical insurance cards, explaining each, and assuring them that some or all would cover absolutely anything they could throw at me.
I had a very pleasant MD and RN and a very sweet student nurse. The student nurse successfully slipped in an IV - but not without a fountain of blood all over. I tried to encourage her the entire time by informing her "you'll have no problem - I have really good veins...that's ok...we all do that the first time...." I could still see her nervous tremor..... and read her mind..." Nurses are the worst patients...."
Two rounds of dilaudid later........no relief. I worried to my husband - they're gonna think I am a junkie or something if I tell them it didn't work. For this very reason I had copies of my Canadian ER visit....dx, bloodwork and all (little did I realize that might make them even more suspicious)
I guess they thought I was not your usual drug-seeker - because I got a chaser of IV morphine......and YAY. Relief. Whoo hoo.Now, can I get this thing outta my arm? I apologised profusely to the nurse who put the IV in - for getting better so quick. By the way, I loved the emesis bag they gave me (much better than those darn chip trays that patients tend to overshoot) and since I didn't have to use it .....I saved it for the ride home, and later took it with me when I eventually had my surgery.
I was given a script for oxycodone - 25 tabs. A little excessive, I thought, but ya never know when this pain might strike again before I get back up to Canada.
The CT scan that I finally had done confirmed gallstones. What with my pain history, I couldn't postpone the inevitable.
I was thinking about the cholecystectomies that I had looked after back in the 80s when I worked on the Surgical unit. They were sliced and diced from front to side to back, HUGE incisions with T-tubes draining and penrose drains with ostomy bags over them, or drains down to bags or bottles and NG tubes for several days. Hospital stays were usually several weeks not the daycare surgery with 3 tiny puncture wounds it is now.
If I was ever grateful for something, I was surely grateful that my gallbladder acted up in the 21st century and NOT when I was working surgical back in the 1980s!
I will keep this entry short.
Suffice to say I had a great experience as a patient in the "hospital of horrors". Funny thing though. After the fact, I kept getting comments from people about the phone calls I made immediately post op from my stretcher in daycare recovery. Apparently I called up and babbled on and on to my several cousins, friends, mother, mother-in-law and God knows who else.
I chastised my husband, "Couldn't you have at least stopped me???" uh. He thought I was totally aware of what I was doing.
Much later, my husband mentioned the male nurse that looked after me in daycare after surgery. "What male nurse?" I inquired with trepidation.
"You know, the one you told all about your work in California, and your experiences in the delivery room, and don't you remember showing him your puke bag you got from your American ER visit......"
I was horrified.
"Ya...." he continued ".....you were talking just normal - just like you are doing right now......"
I NEVER want to be a patient again. EVER.
And Jan, if I ever call you again about any aches and pains......just euthanized me right then and there.


 This tragedy happened at the time when cell phones were just emerging, and no thought or concern was given to talking on a cell while driving. It was just the beginning of many such accidents to come in the community and the country.